
Your shopping cart is empty!
Welcome visitor you can login or create an account.
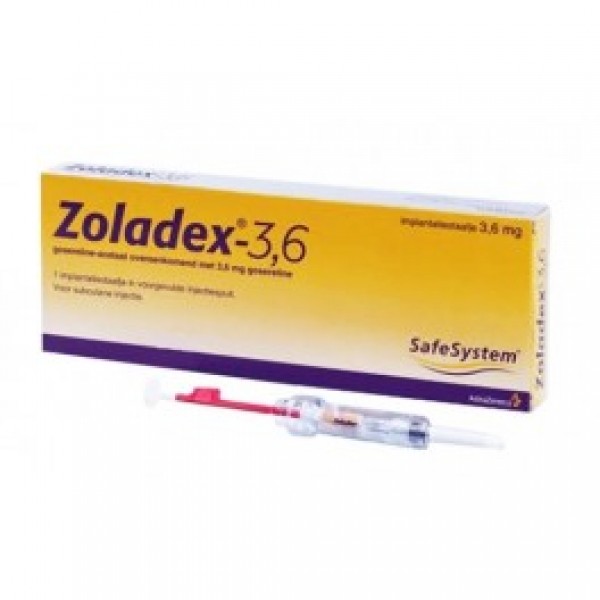
Zoladex depot . 3.6 mg.1amp
Product Code: Zoladex depot . 3.6 mg.1amp
Availability: In Stock
Product viewed: 5219


Zoladex depot. 3.6 mg.1 amp

Composition and dosage form:
Zoladex is a sterile, white to cream-colored cylindrical depot, which gozerelin acetate (equivalent to 3.6 mg gozerelin) is dispersed in a matrix of biodegradable lactide-glycolide copolymer. It is sold in a syringe applicator with a single dose.
Indications:
Prostate cancer: Zoladex is indicated for the treatment of prostate cancer suitable for hormonal therapy.
Breast cancer: Zoladex is indicated for the treatment of breast cancer suitable for hormonal therapy in premenopausal and perimenopausal.
Endometriosis: In the treatment of endometriosis, Zoladex alleviates symptoms, including pain, and reduces the size and number of endometriotic lesions. Thinning of the endometrium: Zoladex is indicated for pre uterine endometrial thinning prior to endometrial resection or ablatsio.
Uterine fibroids: Treatment of fibroids shrink Zoladex lesions improves hematologic status of patients and reduce symptoms, including pain. It is used as adjunctive treatment operations to facilitate surgical techniques and operative blood loss reduction.
Assisted reproduction: Suppression of hypothalamic-pituitary axis in preparation for ovulation induction.
Dosage and method of administration
Adults
A depot of Zoladex 3.6 mg injected subcutaneously into the anterior abdominal wall every 28 days.
Artificial insemination: Zoladex 3.6 mg is administered to suppress the pituitary gland, as determined by serum estradiol levels similar to those seen in the early follicular phase (approximately 150 pmol / 1). This usually takes between 7 and 21 days.
When you achieve suppression begins superovulation (controlled ovarian stimulation) with gonadotrophin. Suppression achieved with agonist depot is more stable, suggesting that in some cases there may be an increased need for HCG. At the appropriate stage of follicular development gonadotropinat stop and apply human chorionic gonadotropin (hCG) to induce ovulation. Monitoring of treatment, obtaining oocytes and fertilization techniques are performed according to usual practice in individual clinic.
There is no need for dosage adjustment in patients with renal impairment.
There is no need for dosage adjustment in patients with hepatic impairment.
There is no need for dosage adjustment in elderly patients.
Endometriosis should be treated only for a period of six months, as there is currently no clinical data for longer periods of treatment. You should not make repeated courses because of the risk of loss of bone mineral substance. It has been shown that in patients receiving Zoladex to treat endometriosis, the addition of hormone replacement therapy (estrogen and progesterone daily) reduces the loss of bone mineral substance and vasomotor symptoms.
When used for thinning the endometrium: you must apply two landfills in four weeks, the surgery was scheduled between zero and the second week of the second depot.
Children
Zoladex is not indicated for use in children.
Contraindications:
Zoladex should not be used in patients with known hypersensitivity to Zoladex or other analogs of LHRH.
Zoladex should not be used during pregnancy or breastfeeding.
Precautions:
Zoladex is not indicated for use in children as safety and efficacy have not been established in this group of patients.
Men
The use of Zoladex in men at particular risk of developing ureteric obstruction or spinal cord compression should be considered carefully and patients should be monitored closely during the first month of treatment. In the presence or development of spinal cord compression or renal impairment due to ureteric obstruction must be specific standard treatment of these complications.
Ladies
The use of LHRH agonists in women can cause loss of bone minerals. Available so far Zoladex data show an average loss of 4.6% of bone mineral substance in the spine after six months treatment with a progressive recovery to an average loss of 2.6% compared to baseline six months after cessation of treatment. It has been shown that in patients receiving Zoladex to treat endometriosis, the addition of hormone replacement therapy (estrogen and progesterone daily) reduces the loss of bone mineral substance and vasomotor symptoms.
Zoladex should be used with caution in women with known metabolic bone disease.
Zoladex can cause an increase in resistance of the cervix, which can lead to difficulties in dilatation of the cervix.
There are currently no data on the effect of treatment of benign gynecological conditions with Zoladex for periods exceeding six months.
Artificial insemination:
Zoladex 3.6 mg should be used only as part of a scheme to artificially inseminated under the supervision of a physician experienced in the field.
As with other agonists of LHRH, there are reports of ovarian hyperstimulation syndrome (OHSS) associated with the use of Zoladex 3.6 mg in combination with HCG. It is suggested that suppression achieved with agonist depot, can in some cases lead to an increased need HCG. Must be carefully monitored stimulation cycle to identify patients at risk of developing OHSS, as the severity and frequency may vary depending on the dosing regimen of gonadotropin. You can not apply human chorionic gonadotropin (hCG), if it is deemed necessary.
Recommended Zoladex 3.6 mg should be used with caution in vitro fertilization in patients with polycystic ovarian syndrome as obtaining follicles may be increased.
Interactions with other medicinal products and other forms of interaction:
None known.
Pregnancy and lactation:
Although reproductive toxicology studies in animals have revealed no evidence of teratological potential Zoladex should not be used during pregnancy as there is a theoretical risk of miscarriage or fetal abnormality if LHRH agonists used during pregnancy. Potentially fertile women should be carefully examined before treatment to exclude pregnancy. Non-hormonal methods of contraception should be used during treatment and in case of endometriosis in the restoration of menstruation.
Should exclude pregnancy before Zoladex 3.6 mg can be used for artificial insemination. Clinical data for these conditions are limited but available evidence it may be presumed that there is no causal link between Zoladex and any subsequent abnormalities in the development of oocytes and pregnancy outcome.
The use of Zoladex during lactation is not recommended.
Effects on ability to drive and use machines:
There is no evidence that Zoladex leads to violation of these activities.
Adverse effects:
General
Rare cases of hypersensitivity reactions, which may include some manifestations of anaphylaxis.
Arthralgia has been reported. Reports of skin rashes which are usually mild and often reduced without interrupting treatment.
In patients using Zoladex were sometimes observed changes in blood pressure, manifest as hypotension or hypertension. Changes are usually transient, resolving with continued therapy or after cessation of therapy with Zoladex. Rarely, such changes were so pronounced that they require medical intervention including withdrawal of treatment with Zoladex.
Separate local effects include pronounced bruising at the site of subcutaneous injection.
Men
Pharmacological effects in men include hot flushes and reduced libido, rarely require discontinuation of therapy. Not very often marked swelling and tenderness of the breasts. In patients with early prostate cancer may experience a temporary increase in bone pain, which can be treated symptomatically. Isolated cases of ureteric obstruction and spinal cord compression.
The use of LHRH agonists in men can cause loss of bone minerals.
Ladies
Pharmacological effects in women include hot flushes, sweating, and loss of libido, which rarely require discontinuation of therapy. Not very often noted headaches, mood changes including depression, vaginal dryness and changes in breast size. In patients with early breast cancer may experience a temporary increase in signs and symptoms that can be treated symptomatically. Women with fibroids may cause degeneration of fibroids. Rarely, patients with breast cancer metastases have developed hypercalcaemia on initiation of treatment.
In vitro fertilization: As with other agonists of LHRH, there are reports of ovarian hyperstimulation syndrome (OHSS) associated with the use of Zoladex 3.6 mg in combination with HCG. It is suggested that the suppression achieved with agonist depot, can in some cases lead to an increased need HCG. Must be carefully monitored stimulation cycle to identify patients at risk of developing OHSS, as the severity and frequency may vary depending on the dosing regimen of gonadotropin. You can not apply human chorionic gonadotropin (hCG), if it is deemed necessary.
Overdose
There is no experience with overdose in humans. From animal experiments it can be assumed that at higher doses of Zoladex can not effect other than the intended therapeutic effect of concentrations of sex hormones on the reproductive tract. In case of overdose, it should be treated symptomatically.
Pharmacological Properties
Pharmacodynamic properties
Mechanism of action: Zoladex (D-Ser (But) 6 Azgly10 LHRH) is a synthetic analogue of the natural LHRH. Following chronic administration of Zoladex to inhibit pituitary secretion of luteinizing hormone, leading to a fall in serum testosterone concentrations in men and serum concentrations of estradiol in women. This effect is reversible upon discontinuation of treatment. Early Zoladex and other agonists of LHRH, may transiently increase serum testosterone concentrations in men and serum concentrations of estradiol in women. During the early stages of treatment with Zoladex some women may experience vaginal bleeding of variable duration and intensity. Such bleeding is bleeding probably due to estrogen withdrawal and is expected to stop spontaneously.
In men, about 21 days after the first depot injection, testosterone concentrations decrease to values kastratni and remain suppressed for treatment every 28 days. This inhibition leads to tumor regression and symptomatic improvement in most patients.
In women, serum concentrations of estradiol inhibit approximately 21 days after the first depot injection and treatment every 28 days remain depressed at levels comparable to those observed in postmenopausal women. This inhibition is associated with response to hormone-dependent breast cancer, endometriosis, uterine fibroids and suppression of follicular development in the womb. It will cause thinning of the endometrium and lead to amenorrhea in most patients.
It has been shown that the Zoladex in combination with iron induces amenorrhea and improves the concentration of hemoglobin and related hematological parameters in women with fibroids who are anemic. The combination produced a mean hemoglobin concentration of 1 g / dL higher than that achieved with iron therapy.
Rarely, some women may enter menopause during treatment with LHRH analogues and may not recover menses after cessation of therapy.
Pharmacokinetics
Bioavailability of Zoladex is almost complete. Administration of a depot every four weeks to ensure the maintenance of effective concentrations no accumulation in tissues. Zoladex is poorly protein bound and has a serum half-life of two to four hours in subjects with normal renal function. The half-life is prolonged in patients with impaired renal function. In this compound, which is introduced in the form of a depot once a month, this change will have minimal effect. Therefore, no adjustment of dosage for such patients. No significant change in pharmacokinetics in patients with hepatic insufficiency.
Preclinical safety data
An increased incidence of benign pituitary tumors in male rats after long-term repeated administration of Zoladex. Although this finding is similar to results reported previously in this species following surgical castration is not detected any difference for people.
In mice, long-term repeated doses being administered in multiples of people were histological changes in some of the digestive system, manifested by hyperplasia of islet cell pancreatic benign proliferative condition in the pyloric region of the stomach, reported as spontaneous lesions in this species.
Write a review
Your Name:Your Review: Note: HTML is not translated!
Rating: Bad Good
Enter the code in the box below:
Related Products
DECAPEPTYL depot amp. 3.75 mg. INGREDIENTS:One pre-filled s..
169.00€